


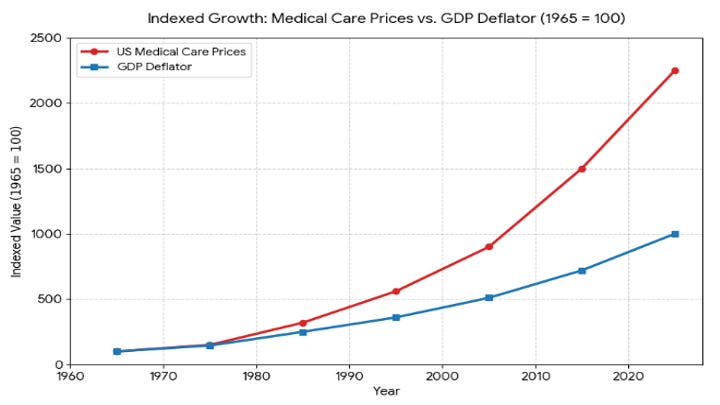
Ultimate success in health reform requires the health sector to look like other growth industries with high productivity increases and lower-than-average price growth.
As with any very large and ever-evolving system, there is no simple, single answer to how government can or should monitor or control healthcare in the United States. Nonetheless, the rise in U.S. healthcare costs to over $40,000 per household in 2026, along with high projected future cost growth, forces policymakers to give renewed attention to cost control. After all, much of that control, or lack thereof, stems from the design of government spending and tax programs that cover the majority of these costs. The Congressional Budget Office recently gave us more bad news about the ineffectiveness of current health policy. It projected that federal subsidies for health insurance over the 2026–2036 period will grow faster than GDP, add up to more than $33.6 trillion, and, despite all that additional money, still leave an increasing portion of the population uninsured.
That the government covers a large portion of healthcare costs doesn’t mean that households don’t feel the full pinch. We pay either directly or through our taxes. These include the higher taxes required down the road when borrowing covers current expenses.
High Prices
The cost of healthcare equals price times quantity, summed across its various goods and services. My purpose here is to emphasize the importance of the price side of this equation in driving up the share of national income spent on healthcare, and to tease out some ways government programs might less encourage that price inflation.
The graph above compares the government’s estimates of increases in health care prices and economy-wide prices from January 1965 to January 2025. While prices for all goods and services rose nearly 8-fold, health care prices rose nearly 18-fold over those 60 years. Put another way, if medical care prices had increased at the same rate as overall inflation, national health care expenditures in the U.S. would be about 8 percent of GDP today, rather than 18 percent. In 1965, with the adoption of Medicare and Medicaid, the federal government began covering a large and growing share of total health costs. This price metric indicates that the increase in real health services the government provided (i.e., the quantity) has been far less than the increase in the amount it has paid. Whatever the limitations of efforts to measure prices, and they are many, the data yield conclusions consistent with separate research indicating that, by many measures, the quality of health care in the U.S. is no greater than in nations that spend far less in both real dollar-equivalent terms and as a share of their GDP.
These data pose a crucial question for healthcare reform: how can it be done in a way that increases the cost-effectiveness of the healthcare sector? To what extent can reform limit future healthcare price inflation while still encouraging improvements in the quality and quantity of healthcare?
I want to be clear. There are no free lunches. If Congress reduces payments to providers, there will be some loss of provision or quality. Some talented people would become engineers instead of doctors if doctors’ salaries grew more slowly. Some drugs would take longer to produce. I applaud health reformers’ attempts to find the healthcare equivalent of the $500 hammers whose elimination would make the Defense Department more efficient; confining health or Defense Department reform efforts only to removing pure waste is quite a limited exercise.
Looking to Other Growth Sectors for an Answer
So, where does this take us? I began by saying that there are no easy answers for how to guide or direct health reform. The U.S. healthcare economy, by itself, is larger than Germany’s economy and no easier to control.
Still, one way to think about solving the healthcare price problem is to look at other growth sectors of the economy. Unlike the healthcare sector, most of these sectors decrease prices or increase them at lower, not higher, rates than overall price inflation. Their lines in the graph above would be well below both medical care price inflation and the GDP deflator.
They achieve these results mainly through competition.
Unlike healthcare, these other growth sectors operate in a more competitive environment and are much more dependent on private funding—what we, not government, pay directly. Because households face budget constraints, companies in these other industries compete both internally within their industry and externally with other industries for the same dollars. Thus, Microsoft competes not only with Apple but with your local grocery store chain.
Not so with healthcare. Government-provided healthcare programs operate without effective budget constraints. Many providers simply need to get the government to accept some new procedure or drug at a price many individuals would never pay on their own.
In theory, of course, all government programs would compete with each other for uses of your tax dollar. Congress, however, has granted healthcare programs a level of automatic growth not allowed for almost all other programs, especially those that must go through an annual appropriations process.
A similar problem exists with employer-provided insurance. Employers are limited by law in how much they can offer competitive plans and in how much employees can pocket by picking a lower-cost plan. Moreover, low- and moderate-income employees—those less likely to buy high-cost plans because of their greater need to spend their compensation for other basic needs—cannot turn to the Exchanges set up by Obamacare, buy a lower-cost plan, and pocket what the employer would have spent on their behalf.
***
In sum, health reform must address the unsustainable growth in healthcare costs. Restraining excessive price increases will be key. Figuring out ways to promote greater competition offers avenues to limit those price increases while encouraging providers to do more for less, not simply less. However achieved, success generally means continued productivity growth—better healthcare—with less price growth.
American healthcare has one part where prices are
actually restrained. It is not the competitive part.
Medicare sets its rates by publication. Hospitals ran a
negative 12.1 percent fee-for-service Medicare margin in
FY2024, and take about 82 cents for every dollar of cost.
That is real discipline. It comes from a price list.
Medicare Advantage is the same government doing the same
job by competition instead. Plans bid, beneficiaries
choose, the average county offers dozens of options.
MedPAC projects payments at 114 percent of fee-for-service
in 2026, roughly 76 billion above. About 57 billion of
that is favourable selection and 22 billion is coding.
Strip both out and it lands near 99 percent.
Same payer, same patients. One method underpays. The
other overpays by 76 billion.
Competition does lower hospital prices where it still
exists. Monopoly hospitals run about 12 percent above
markets with four or more rivals. But 90 percent of metro
areas are already highly concentrated for hospitals. So
promoting competition there means antitrust and entry
policy, not a lever available this budget cycle.
There is also a two-sided problem. More insurer
competition lowers premiums and weakens the only party
that bargains hospital prices down. You cannot raise
competition on both sides and expect both numbers to fall.
The variable doing the work in your examples is not
rivalry. It is whether anyone in the transaction is
minimising cost. A fixed price does that. Competition
then decides who gets the volume.
I don't disagree, though I'm not sure how meaningful that graph is. I haven't examined the issue closely for some years, but I'm quite confident that over decades, a substantial chunk of the rise in healthcare prices resulted from from failure/inability to properly adjust for quality. I just had two outpatient surgical procedures that, just 25 years ago would have demanded extended hospital stays, much more pain than the quite-tolerable amount I encountered, and the likelihood of future surgeries as the original fixes failed. I wrote this piece 32 years ago, but the message still holds: https://www.richmondfed.org/-/media/RichmondFedOrg/publications/research/economic_quarterly/1994/fall/pdf/graboyes.pdf